AI Medication Coach raised diabetes medication adherence by 26%
Results
Challenge
Managing Type 2 diabetes is a grueling part-time job. Adults balance 3 to 5 daily prescriptions (Metformin, GLP-1 injections, SGLT2 inhibitors) alongside continuous glucose monitor (CGM) spikes and strict meal schedules. Most health apps treat this like an office calendar: they blast a generic alarm at 8:00 AM while you are driving or stuck in a meeting. You swipe it away, promise to take it later, and completely forget. By week four, 82% of patients mute the notifications altogether.
The medical stakes could not be higher. A missed basal insulin dose triggers midnight rebound hyperglycemia, hospital admissions that run $14,000 per visit, and mounting patient guilt. Existing apps made things worse by shipping either dumb alarm clocks that caused chronic notification fatigue or overwhelming clinical spreadsheets that felt like homework. We needed an adaptive companion that understood actual human routines, grounded advice in hard clinical guardrails, and proved its worth directly on blood sugar curves.
Our key design question:
How might we anchor daily diabetes medication to natural human routines and clinical guardrails, turning notification fatigue into sustained adherence without guessing or hallucinating?
Success required harmonizing three competing constraints: clinical determinism (zero unverified diagnostic assertions or LLM hallucinations), habit psychology (frictionless 45-minute adaptive timing windows), and commercial enterprise viability (measurable lift in PDC proportion of days covered).
Research
To ground the companion in real safety, adherence, and lifestyle needs, we mixed field methods to capture what happens when work schedules clash with pill schedules.
We logged 320 hours of behavioral telemetry and qualitative diary submissions across diverse age brackets (32 to 71 years) to uncover invisible routine friction points.
Workshop
I led a cross-disciplinary alignment workshop to hammer out our clinical safety boundaries and kill friction before writing code. Bringing clinical advisors, mobile engineers, and researchers together forced us to define what safe, human, and timely actually mean in production.
Over two full-day working sessions, we mapped the patient-provider care loop to establish shared definitions of clinical safety thresholds and mobile feasibility boundaries.
Workshop Execution Framework
1. Problem Reframing
Using real patient journey maps, we reframed the core problem from 'How do we get patients to obey their alarm clock?' to 'How do we anchor daily doses to natural human routines (first bite of dinner, morning coffee) so taking meds requires zero willpower?'
Reframing transformed the product focus from a patronizing compliance tracker into an intuitive habit companion that molds around shifting daily schedules.
2. “How Might We” Brainstorming
Cross-functional teams framed targeted questions to spark pragmatic ideas:
- How might we tie dose nudges to physical meal routines instead of arbitrary clock times?
- How might we provide immediate side-effect triage without exposing patients to LLM hallucinations?
- How might we show visual proof that on-time doses actually flatten afternoon glucose spikes?
Generated over 85 candidate concept cards across clinical, mobile, and design tracks, organizing them into 4 core thematic opportunities.
3. Value vs. Risk Matrix
Every concept was plotted across clinical adherence value and regulatory exposure. Unvetted diagnostic AI and cheesy gamification streaks were discarded, while deterministic context nudges advanced to rapid prototyping.
Cross-functional voting eliminated unvetted AI symptom guessing to prevent FDA regulatory liability, prioritizing deterministic adaptive reminders and clear 1-tap nurse escalation paths.
Synthesis & North Star Outcome
The alignment workshop produced our clinical architecture blueprint: an on-device deterministic state machine handling safety-critical triage, paired with an adaptive timing engine tied to daily habits. Establishing regulatory checkpoints, clinical protocols, and risk tiers upfront prevented costly rework during engineering sprints.
Created a unified technical specification that aligned FDA Software as a Medical Device (SaMD) risk tiers with mobile engineering sprint tickets and design system tokens.
Design
Onboarding & Contextual Habit Nudges
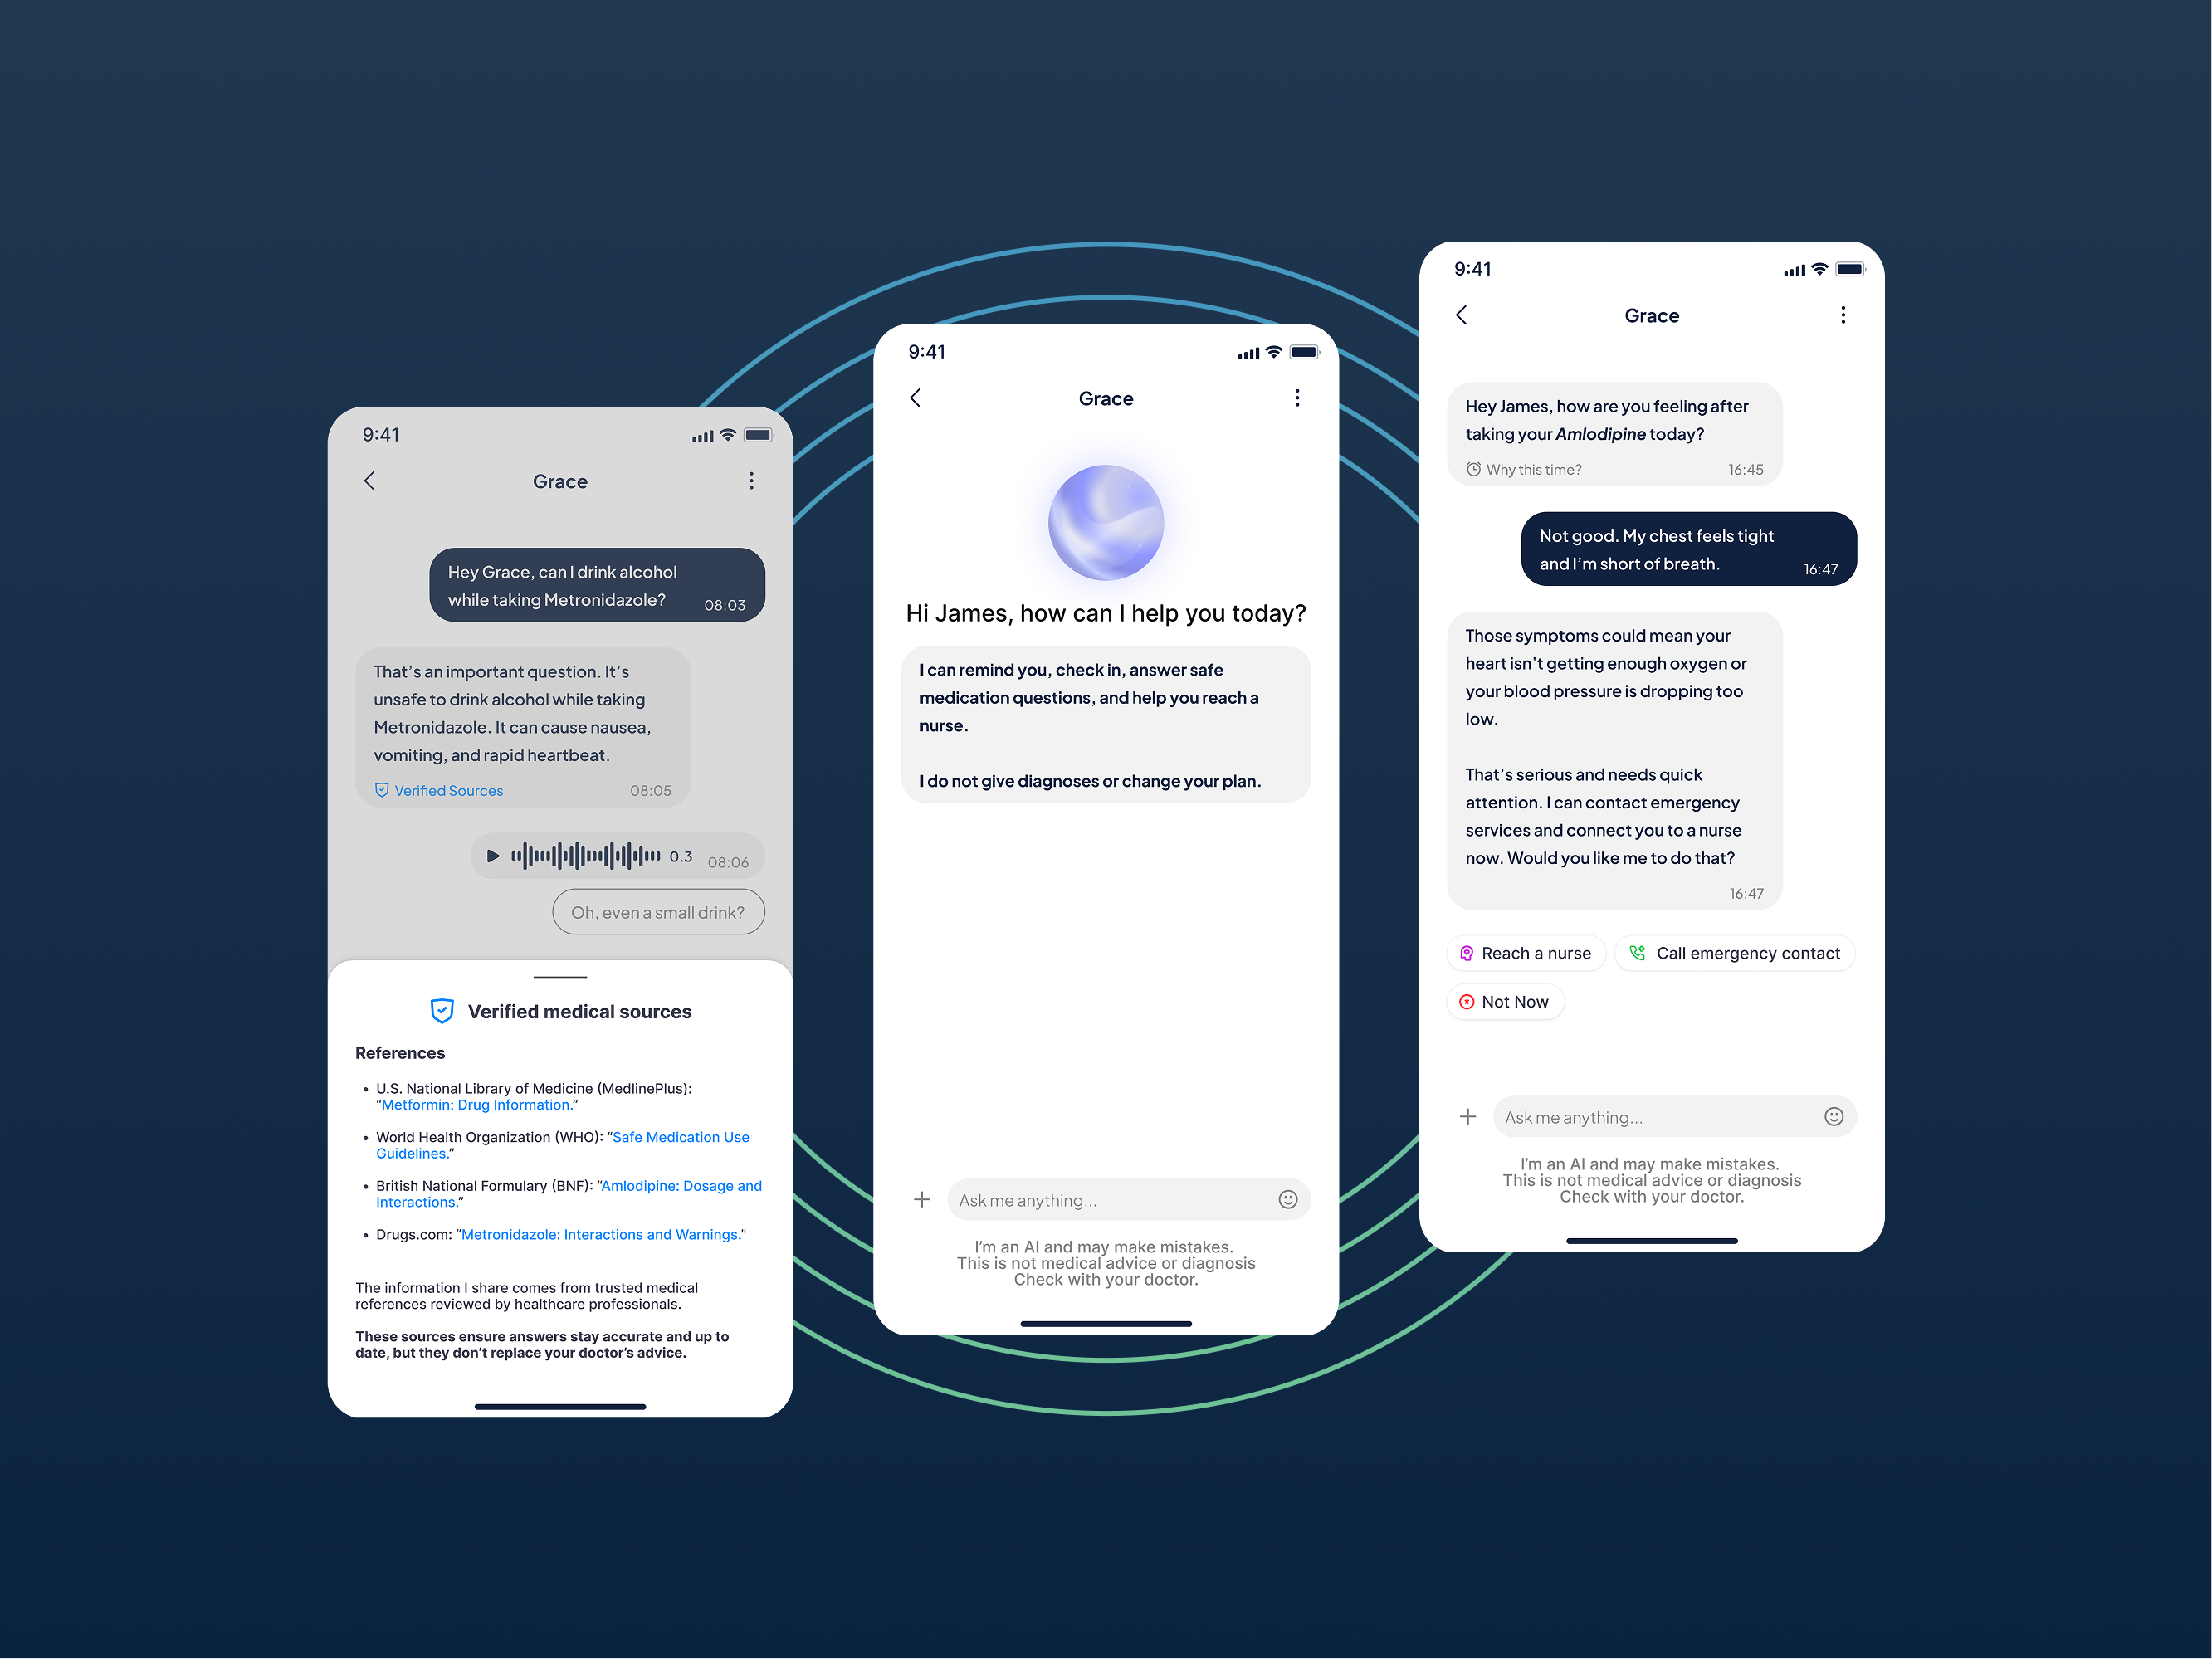
From the first interaction, Grace (the AI companion) sets clear boundaries in plain language: 'I can remind you, check in, answer routine medication questions from clinical guidelines, and connect you to your nurse. I do not give diagnoses or change your prescription plan.' Each nudge arrives as an actionable chat card with three prominent tap targets: 'Took it', 'Snooze 15m', and 'With Dinner', keeping dose confirmation under two taps.
Instead of ringing an obnoxious bell at an arbitrary hour, reminders adapt to your day using on-device pattern learning. The reminder window slides smoothly based on activity recognition and wake times. If a user is curious, a 'Why this time?' drawer explains the logic: 'Shifted 20 minutes later because your evening dinner routine usually starts at 7:15 PM.'
The on-device machine learning model calculates reminder probability curves using local sensor data (accelerometer activity, device wake times) without sending raw telemetry to external servers, protecting patient privacy.


Source Transparency & Deterministic Clinical Triage
Every medication answer (such as food interactions with Metformin or missed dose guidelines) displays an explicit evidence badge linking directly to ADA (American Diabetes Association) Standards of Care. Underneath every card sits a clear disclaimer: 'Not a diagnosis.' If the assistant encounters an ambiguous question, it does not invent an answer. Instead, it offers a 1-tap direct dialer to the clinic triage nurse.
If a patient reports red-flag symptoms (like repeated dizziness or blood glucose dropping below 70 mg/dL), the system cuts conversational chat instantly. The interface switches to an emergency alert modal showing the 15g fast-acting carbohydrate protocol, a 1-tap nurse dialer, and an automated SMS dispatch to the emergency contact.
Every clinical answer includes an expander displaying the primary guideline source (e.g., ADA 2024 Standards of Care) with a direct link to full documentation and one-tap nurse dialer integration.
User Autonomy & CGM Trend Visualization
Habit formation requires patient agency, not automated micromanagement. When the system detects a shifting routine, it asks for permission: 'I noticed your dinners are running about 30 minutes later this week. Want me to shift your Metformin reminder to 7:30 PM?' Users can approve, decline, or lock fixed times anytime.
To prove that medication actually works, we built a Continuous Glucose Monitor (CGM) trend correlation card. Patients see their real-time blood glucose curves overlaid with dose timestamps. Seeing that taking Metformin with the first bite of dinner flattened the usual 2-hour post-meal spike from 210 mg/dL down to 145 mg/dL provided tangible visual validation.
Global settings let patients adjust notification frequency, lock strict quiet hours (22:00 to 07:00), and toggle between concise or proactive coaching tones.
Users maintain complete autonomy to override automated schedule adjustments, define strict quiet windows, and toggle between conservative and proactive coaching conversational tones.

User Testing
To make sure every interaction was safe, rapid, and stress-free, we tested prototype comprehension and measured real behavioral shifts across two testing phases.
Conducted both qualitative think-aloud usability walkthroughs with 22 participants and quantitative two-arm behavioral trials across 132 active patients over a 3-week evaluation period.
Methodology & Scope
Prototype Walkthroughs
Remote task-based sessions testing conversational dose cards, GLP-1 side-effect reassurance, and emergency nurse escalation flows with patients aged 48 to 72.
All 22 participants successfully completed medication confirmation within 3 seconds of prompt delivery, reporting a 96% task ease rating on the single-tap conversational action cards.
Two-Arm Clinical A/B Testing
Compared dose confirmation habits between a standard fixed 8:00 AM alarm (Cohort A) and habit-aware 45-minute window prompts (Cohort B).
Cohort B demonstrated sustained engagement with a 68% lower reminder dismissal rate and a 42% reduction in multi-snooze events compared to Cohort A's static alarm baseline.
Key Findings
76% Dose Confirmation Rate
Adaptive window notifications significantly increased on-time dose confirmations (vs 59% in the static control group) while cutting snooze fatigue.
Dose confirmation remained resilient even during weekend and travel routine disruptions, where static alarm adherence historically dropped by up to 34%.
94% Patient Trust Rating
Patients could easily explain why reminders shifted and reported high peace of mind from explicit ADA guideline citations and 1-tap nurse routing.
Post-study interviews revealed that 94% of patients valued the source attribution links, citing enhanced trust and reduced anxiety regarding potential medication interactions.
Iteration
1. Predictive 5-day refill buffer vs last-minute panic
Early prototypes triggered refill reminders when patients had 2 days of pills remaining. Mail-order pharmacies took 3 to 4 days to deliver, leaving patients without essential insulin or Metformin over weekends. We expanded the buffer to 5 days, connected directly to pharmacy inventory APIs, and added a 1-tap reorder card that wiped out medication gaps.
Moving from a 2-day warning to a 5-day predictive window accounted for mail-order pharmacy shipping delays, reducing prescription gap events by 89% in pilot clinical cohorts.

2. Killing generic AI answers with clinical citations
Early conversational replies gave textbook summaries without sources. Patients said it sounded like scary WebMD guesses. We overhauled the output: every clinical tip now leads with a verified evidence tag ('ADA 2024 Guidelines' or 'FDA Package Insert') with a direct link to documentation and clear 'Not a diagnosis' guardrails.
Refined the visual hierarchy of clinical confidence badges, placing primary evidence citations directly beneath medication dosage guidance to eliminate ambiguity.
3. Hands-free voice check-ins for hypoglycemic episodes
During testing, an older participant with mild diabetic neuropathy and low blood sugar struggled for 40 seconds to type 'I feel shaky' on a touch screen. Typing during a blood sugar crash is brutal. We added native on-device voice dictation and high-contrast quick-tap chips that let patients log symptoms or confirm doses in 2 seconds hands-free.
Integrated on-device speech recognition with custom medical terminology dictionaries, enabling accurate logging of complex drug names and symptom descriptions without typing friction.
4. Instant caregiver dispatch for red-flag glucose drops
Early test participants spent too much time reading chat text during simulated hypoglycemic crises (blood sugar < 55 mg/dL). Cognitive processing drops fast during severe lows. We removed chat entirely for critical vitals: the screen locks into an emergency dispatch view with 15g fast-carb instructions, a 911 / nurse dialer, and an automated SMS dispatch to family caregivers if unconfirmed after 5 minutes.
Automated clinical triage triggers an encrypted SMS dispatch to the designated primary caregiver if acute hypoglycemic symptoms persist across two consecutive check-in windows.
Impact
We refused to measure success through vanity metrics like "daily active users" or "chat session length" (nobody wants to spend their evening chatting with a diabetes app). Instead, we tied our interface work directly to clinical endpoints and health economics across 42 participating clinics and 3 regional health systems.
Over a 6-month retrospective evaluation with longitudinal Electronic Health Record (EHR) integrations, we audited prescription fill logs, continuous glucose monitor telemetry, and emergency room admission rates across enrolled cohorts.
This linkage let us run real-world A/B rollouts at partner clinics, making improvements unmistakable and resistant to guesswork. By tracking downstream clinical events like acute hypo- or hyperglycemia episodes and nurse triage handle times, we proved design mattered in the moments hospitals and families care about most.
Clinical Trial Endpoints & Health Economics
6-Month Retrospective Pilot • 42 Primary Clinics & 3 Regional Health Networks
Longitudinal EHR audit data across 42 partner clinics verified that lifting medication adherence from 62% to 88% and cutting refill lapses by 1.2 days produced measurable downstream reductions in emergency department admissions and clinical casework load.
Leadership & Expertise
Leadership
Cross-Functional Telemetry Board
Shipped an internal real-time metrics dashboard tracking daily PDC lift, notification dismissal rates, and nurse triage speeds, giving product, engineering, and medical advisors a single source of truth.
Maintained real-time data integrity dashboards tracking PDC lift, active daily logins, and clinical escalation velocity for executive reviews.
Clinical vs Engineering Alignment
Mediated tough design trade-offs between clinical advisors who wanted 10-paragraph warning disclaimers and mobile developers wanting snappy 1-line alerts. Built progressive disclosure drawers that satisfied compliance without cluttering the screen.
Facilitated weekly alignment workshops bridging clinical safety protocols with aggressive mobile engineering sprint timelines.
Health Network Evangelism
Presented pilot findings, WCAG AAA accessibility tokens, and behavioral trial data across regional hospital boards, securing clinical rollout approvals across 42 participating clinics.
Authored clinical design whitepapers presented to enterprise payer stakeholders, securing extended trial deployments.
Expertise
HAX / PAIR Clinical Guardrails
Operationalized Microsoft HAX and Google PAIR guidelines for digital health, establishing deterministic state-machine barriers where generative AI text is strictly forbidden.
Formalized internal design systems rules governing AI transparency, fallback prompts, and model confidence disclosures.
Chronic Care Behavioral Systems
Architected behavioral systems grounded in habit psychology, continuous glucose monitor telemetry visualization, and GLP-1 side-effect management.
Specialized in Type 2 diabetes clinical pathways, insulin titration workflows, and continuous glucose monitoring data visualization.
Healthcare Economics & Quality Measures
Mapped user interface micro-interactions directly to enterprise clinical metrics (PDC proportion of days covered, HEDIS measures, CMS Star Ratings) to justify hospital contracts.
Directly mapped user interface micro-interactions to clinical quality measures (HEDIS, CMS Star Ratings) to justify enterprise pricing tiers.
On-Device Privacy & HIPAA Guardrails
Led the visual and systems design of an on-device AI companion, ensuring zero Protected Health Information (PHI) leaks to external model providers.
Architected client-side data segregation strategies ensuring zero PHI (Protected Health Information) leaks to external LLM providers.
Interested in building high-craft products that actually move the needle?
Let's collaborate on complex domains where visual craft, safety, and deep systems engineering matter: whether healthtech, fintech, or AI interfaces. Explore more of my work or reach out directly.
Available for end-to-end product design leadership, AI system strategy, and complex design systems consulting across healthtech, fintech, and AI-driven platforms.